
Recurrent Pregnancy Loss and Genetic Testing: What Couples Should Know
Recurrent pregnancy loss affects about 1–2% of couples trying to conceive. This guide explains where genetics fits in — embryo aneuploidy, parental balanced translocations, and how PGT-A and karyotype testing may help, with realistic expectations.
What counts as recurrent pregnancy loss
Recurrent pregnancy loss (RPL), sometimes called recurrent miscarriage, is generally defined as two or more clinically recognized pregnancies that end before 20 weeks of gestation. A single early loss is common and usually a one-time event. When losses repeat, however, many couples naturally ask whether something underlying is causing it — and genetics is one of the first places clinicians look.
It is worth saying plainly at the start: having more than one loss does not mean you will never carry a pregnancy to term. Most people who experience recurrent loss do go on to have a child, often with targeted testing and support.
How often does it happen
Roughly 1–2% of couples who are trying to conceive will experience two or more losses. A first-trimester loss affects about 10–20% of known pregnancies, so one loss alone is not unusual. The chance that any given loss has a genetic cause rises with the mother's age, because egg quality and chromosome sorting decline over time.
Understanding the frequency helps put the experience in perspective. Recurrent loss is a real medical pattern, not a reflection of anything a person did wrong.
Where genetics fits in
The majority of early pregnancy losses are driven by chromosomal problems in the embryo itself. These are almost always random events that occur when an egg or sperm is formed, or when the early cells divide. They are not usually inherited from the parents in a way that repeats across every pregnancy.
There are three main genetic angles your care team may consider:
- Embryo chromosomal abnormalities (aneuploidy)
- Parental balanced translocations
- Rare single-gene or medical conditions
Embryo chromosomal abnormalities (aneuploidy)
Most first-trimester losses involve an embryo with the wrong number of chromosomes — a condition called aneuploidy. This can mean a missing chromosome or an extra copy. Aneuploidy usually prevents the pregnancy from developing normally, leading to a miscarriage.
Because aneuploidy is so common in early losses, testing the chromosomes of embryos before transfer can be relevant for some couples. This is where preimplantation genetic testing for aneuploidy comes in.
Preimplantation genetic testing for aneuploidy (PGT-A)
PGT-A examines embryos created through IVF for the correct number of chromosomes before one is transferred to the uterus. In selected groups — particularly those with repeated loss or advanced maternal age — PGT-A may lower the chance of transferring an embryo that is unlikely to result in a continuing pregnancy. You can read more about what PGT-A tests and what the evidence shows.
It is important to keep expectations realistic. PGT-A can reduce the rate of aneuploidy-related loss, but it does not prevent every loss, and it does not improve the underlying chromosome-sorting process. It is a screening tool, not a guarantee.
The embryo biopsy step
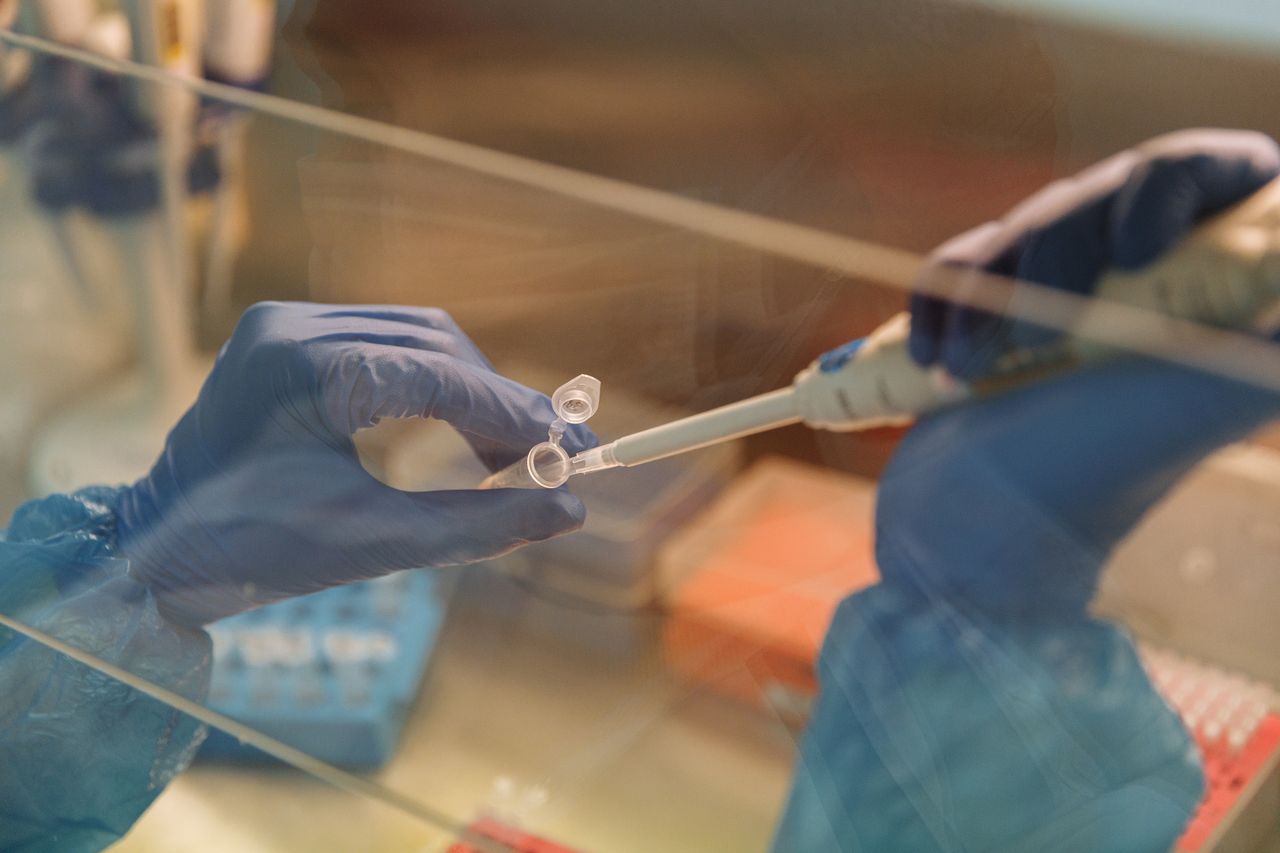
PGT-A requires a small sample of cells, taken from the outer layer of a blastocyst in a process called embryo biopsy. The biopsied embryo is then frozen while the sample is analyzed. A separate, unaffected embryo can later be thawed and transferred.
This step adds laboratory work and cost to an IVF cycle, which is why it is offered selectively rather than to every patient.
Parental balanced translocations
In a smaller subset of recurrent loss, one partner carries a balanced translocation — a rearrangement of chromosomal material where no genetic information is lost. The parent is healthy, but when chromosomes are passed to an embryo, the balancing can go wrong, producing an embryo with too much or too little material.
A simple blood test called a karyotype, done for both partners, can detect this. If found, a reproductive specialist can discuss options including PGT-A or PGT for structural rearrangements.
What the evidence shows
Research suggests that for certain couples, screening embryos for chromosome number can reduce the rate of another miscarriage caused by aneuploidy. The effect is not universal, and not every study agrees on the size of the benefit. What is consistent is that testing is most useful when there is a clear, identifiable pattern — repeated losses, known translocation, or advancing age.
No test can promise a live birth. Counseling that is honest about both the potential and the limits of testing is a core part of good care.
Beyond genetics: other contributors
Genetics explains many, but not all, recurrent losses. Other factors your clinician may evaluate include:
- Uterine structure, such as fibroids or a septum
- Thyroid or other hormone imbalances
- Blood-clotting (thrombophilia) conditions
- Age-related egg quality, which relates closely to markers like AMH and antral follicle count
Because causes overlap, a thorough evaluation usually looks at several systems rather than a single test.
When to seek specialized care
If you have had two losses, it is reasonable to ask your obstetrician or a fertility clinic about an evaluation. After three losses, most guidelines recommend a full workup rather than waiting. Earlier testing is often offered when a known risk factor is present, such as older maternal age or a previous pregnancy affected by a chromosomal issue.
Building a plan with a specialist
A reproductive endocrinologist can help tailor the workup to your history. For many couples, a structured plan — karyotypes, PGT-A when appropriate, and attention to uterine and hormonal factors — improves the odds of a continuing pregnancy. Comparing how clinics approach recurrent loss and reviewing published success rates can also inform decisions.